Physical therapy is designed to rebuild strength, restore mobility, and help patients recover after orthopedic surgery, catastrophic collisions, or chronic pain conditions. Patients place immense trust in their physical therapists and rehabilitation clinics, expecting clinical interventions that adhere to careful, physician-directed protocols.
While rehabilitation naturally involves discomfort and physical exertion, it should never result in severe, avoidable injuries caused by substandard care. In both Idaho and Washington State, physical therapists are licensed healthcare providers held to legally enforceable standards of care. When a provider’s negligence leads to torn surgical repairs, debilitating falls, severe burns, or unrecognized life-threatening emergencies, injured individuals have the legal right to seek accountability through a medical malpractice claim.
Understanding the legal framework and common forms of physical therapy negligence can help patients identify when routine rehabilitation may cross into actionable malpractice.
4 Examples of Potential Physical Therapy Negligence
Physical therapy malpractice claims rarely stem from a simple lack of patient improvement. Instead, they typically arise from affirmative breaches of clinical safety protocols, failure to respect surgical limitations, or a total breakdown in patient monitoring.
1. Aggressive Manual Manipulation and Exceeding Post-Surgical Restrictions
Following orthopedic interventions—such as rotator cuff repairs, ACL or meniscus reconstructions, spinal fusions, or total joint replacements—the operating surgeon issues specific post-operative protocols. These protocols dictate strict restrictions on passive versus active range of motion (ROM), weight-bearing limits, and allowable degrees of flexion or extension during each recovery phase.
When a physical therapist fails to review surgical operative notes, ignores written physician restrictions, or applies excessive manual force to break through scar tissue:
-
Repaired tendons and ligaments can re-tear, necessitating revision surgeries.
-
Surgical anchors, screws, and hardware can dislodge or fracture adjacent bone.
-
Patients often face permanent loss of function, extended downtime, and irreversible chronic pain.
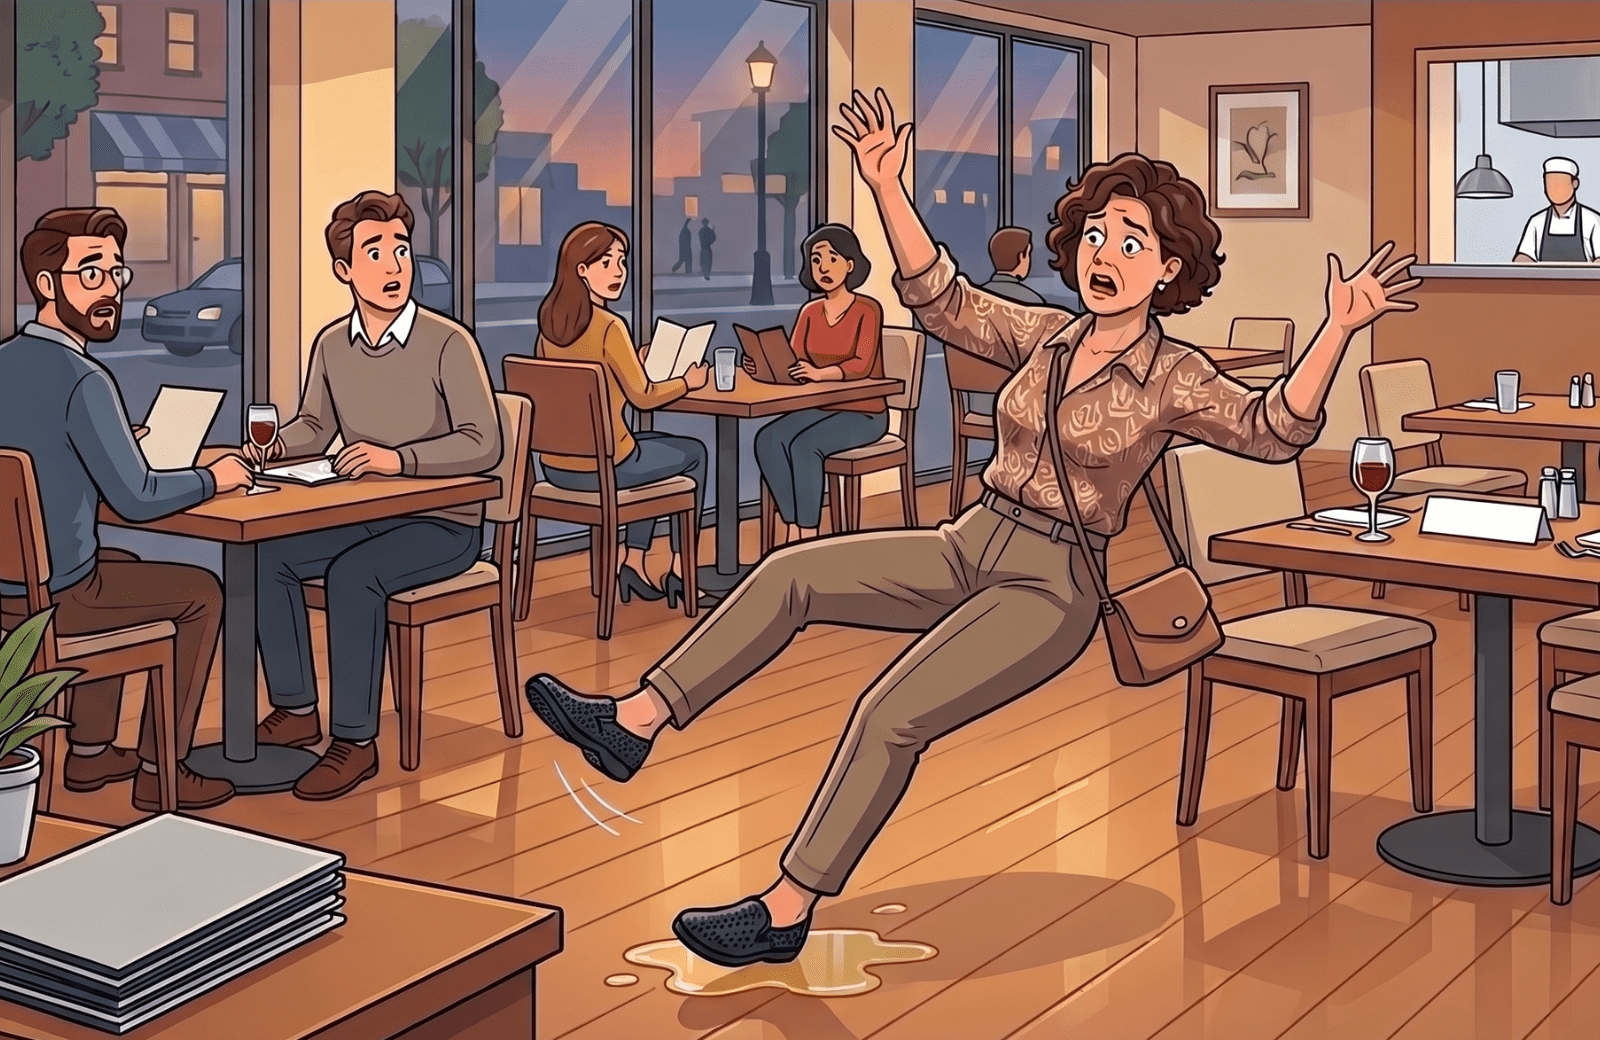
2. Failure to Monitor and Patient Falls
Rehabilitation facilities treat individuals experiencing muscle weakness, vestibular dysfunction, gait instability, and cognitive side effects from post-operative medications. Physical therapists and therapy assistants have a duty to assess fall risk and maintain adequate contact guarding during high-risk exercises.
Actionable malpractice often occurs when staff:
-
Leave a dizzy, balance-compromised, or elderly patient unattended on elevated examination tables, wobble boards, or Swiss exercise balls.
-
Fail to use a gait belt during ambulation training.
-
Leave a patient unmonitored on active motorized equipment (such as treadmills or stationary bicycles), resulting in high-impact falls, secondary hip fractures, subdural hematomas, or spinal trauma.
3. Improper Application of Clinical Modalities
Physical therapy clinics routinely employ adjunct modalities to manage inflammation, relieve spasms, and stimulate neuromuscular function. However, modalities that alter tissue temperature or deliver electrical current carry inherent risks if mismanaged:
-
Thermal Modalities (Hot Packs & Cold Therapy): Commercial hydrocollator packs are stored in water heated between 160°F and 170°F. Failing to place the appropriate number of towel layers between the pack and the patient, or leaving a pack in place while a patient falls asleep, can cause severe second- or third-degree burns requiring skin grafting.
-
Electrical Stimulation (TENS/NMES): Misplaced electrodes, improper unit calibration, or leaving a patient unmonitored during high-intensity electrotherapy can inflict painful burns or localized tissue damage.
-
Dry Needling: Inserting solid filiform needles without proper anatomical precision can puncture underlying visceral structures, leading to catastrophic complications such as an iatrogenic pneumothorax (collapsed lung) or peripheral nerve transection.
4. Failure to Recognize Red Flags and Refer Out
Physical therapists are trained to recognize systemic medical emergencies and complications that mimic musculoskeletal pain. When an emergency arises, a therapist must halt therapy immediately and refer the patient for urgent physician evaluation.
Failing to recognize and act upon clinical “red flags” can turn a treatable condition into a catastrophic or fatal outcome:
-
Deep Vein Thrombosis (DVT) & Pulmonary Embolism (PE): Post-surgical patients are at high risk for blood clots. If a patient presents with unilateral calf warmth, swelling, and localized tenderness, aggressive passive calf stretches or deep tissue massage can dislodge the thrombus into the pulmonary arterial bed, causing a fatal pulmonary embolism.
-
Cauda Equina Syndrome: Patients receiving physical therapy for lumbar disc pathology who report new-onset saddle anesthesia, urinary retention, or bowel dysfunction require immediate emergency surgical decompression. Continued physical therapy without an emergency referral risks permanent neurological impairment and lifelong paralysis.
-
Occult Fractures & Infection: Ignoring progressive, non-mechanical pain, unexplained fever, or inability to bear weight can allow undiagnosed fractures or joint infections (septic arthritis) to worsen unchecked.
Key Steps to Take if You Suspect Physical Therapy Malpractice
If you or a family member experienced a sudden, severe deterioration in health or sustained a new injury during or immediately following physical therapy:
-
Seek Immediate Medical Attention: Consult your orthopedic surgeon or an independent medical doctor to diagnose and document the new injury. Emphasize that the acute symptoms began during a specific rehabilitation exercise or modality.
-
Obtain Your Complete Treatment Records: Request copies of your complete physical therapy chart—including daily encounter notes, flowsheets, modality logs, therapist subjective/objective assessments, and intake documentation. Also request the underlying surgeon’s operative report and referral orders.
-
Preserve Physical Evidence: Take dated photographs of any visible bruising, burns, swelling, or surgical incisions immediately following the incident.
-
Consult an Experienced Medical Malpractice Attorney: Medical malpractice actions in Idaho and Washington are subject to strict statutes of limitations and stringent procedural hurdles. An attorney familiar with healthcare negligence in both jurisdictions can evaluate your records, consult qualified medical experts, and determine whether a actionable breach of the standard of care occurred.
Attorney Advertising & Legal Disclaimer:
This blog post is published for general educational and informational purposes only and does not constitute legal or medical advice. Reading this article or contacting this firm does not establish an attorney-client relationship. Every legal matter depends on its unique facts, and prior case results do not guarantee a similar outcome. Legal services are provided by attorneys licensed in Idaho and/or Washington State.